In brief — the direct answer
Fetal Doppler ultrasound assesses blood-flow waveforms in selected vessels. Umbilical artery Doppler helps assess placental resistance; MCA measurements can assess redistribution or, using peak systolic velocity, the risk of anaemia. These are different measurements with different meanings. Interpretation uses gestation, a specified reference, growth, fluid, heart-rate monitoring and maternal health. Doppler does not directly measure the baby’s oxygen level or guarantee wellbeing.
What is Umbilical Artery & MCA Doppler?
Umbilical artery PI and end-diastolic flow help identify increased placental resistance. MCA PI and the cerebroplacental ratio (MCA PI divided by umbilical artery PI) may indicate redistribution, sometimes called brain-sparing; they do not prove brain injury or exclude it. MCA peak systolic velocity, usually reported as multiples of the median, is used for a different question: possible fetal anaemia. Ductus venosus assessment has a role in selected specialist pathways, particularly very early severe FGR.
Who is at risk?
Doppler may be indicated with suspected FGR, placental disease, red-cell antibodies or particular twin complications. The vessel and frequency depend on the question. Reduced movements need prompt maternity assessment; a Doppler appointment alone is not a substitute for triage and the appropriate fetal assessment.
How we diagnose it
A technically valid waveform, correct vessel and sampling site, gestational age and appropriate reference are essential. A centile, ratio or MoM must be interpreted with its named reference and clinical indication. Guidelines differ in routine use of MCA/CPR and ductus venosus in FGR; explain which protocol applies. A borderline or unexpected result may require repeat expert measurement.
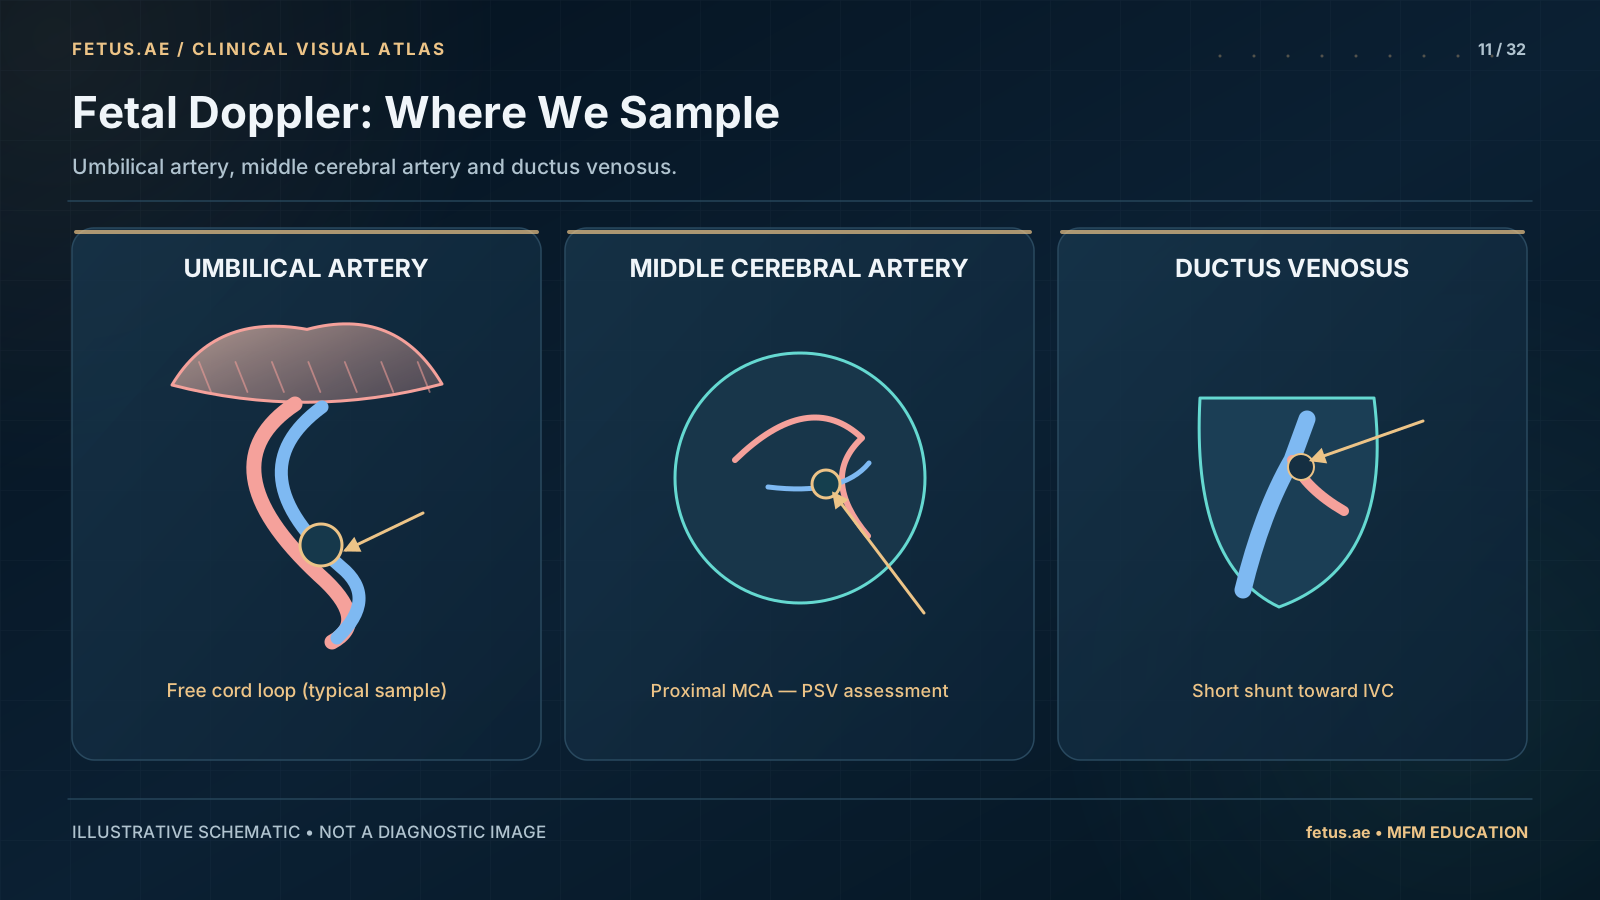 Enlarge schematic
Umbilical artery, middle cerebral artery and ductus venosus.
Simplified educational schematic; not to scale or for diagnosis.
What does management involve?
High resistance may prompt closer surveillance. Absent or reversed umbilical artery end-diastolic flow needs urgent specialist assessment and often intensified monitoring or admission. Delivery timing considers gestation, persistence, fetal heart-rate findings, growth and maternal condition. It is not determined by a universal rule of delivery within hours. Steroids, neuroprotection and neonatal consultation may be indicated if early birth is anticipated.
What are the outcomes?
Doppler-informed surveillance can improve decisions in high-risk pregnancy, but it cannot eliminate stillbirth or all neonatal harm. A normal result is reassuring only within the assessment and time at which it was obtained. Keep follow-up appointments and report reduced movements or new symptoms even after a reassuring test.
When to see a subspecialist
Request prompt review of abnormal Doppler, suspected growth restriction or possible fetal anaemia. Reversed flow or concerning fetal/maternal symptoms warrants urgent maternity assessment. Ask which vessel is abnormal, the gestation-specific interpretation, the next test and the changes that would lead to admission or delivery.