In brief — the direct answer
Pre-eclampsia risk assessment helps identify pregnancies that may benefit from prevention and closer surveillance. A first-trimester combined model can use maternal history, standardised blood pressure, uterine artery Doppler and placental biomarkers. It estimates risk, not a diagnosis or a guarantee. Performance depends on the outcome being predicted, the model, inputs and population; “accuracy” is not a single universal percentage.
Predicting the Unpredictable: The Biology of Pre-eclampsia
First-trimester pre-eclampsia screening is an advanced predictive evaluation designed to identify pregnancies where the placenta may not be functioning optimally. Although high blood pressure usually manifests in the second or third trimester, the 'seeds' of pre-eclampsia are sown during the first 12 weeks of pregnancy when the placenta embeds into the uterine wall.
If the placental blood vessels (spiral arteries) do not transform correctly, the placenta remains under stress, releasing factors into the mother's bloodstream that lead to systemic inflammation and vascular damage. This is what we call pre-eclampsia. In our Unit, we moved beyond basic risk factor checklists and utilize the 'Triple Test' during the 12-week window. This evaluates:
- Mean Arterial Pressure (MAP): Blood pressure measured in both arms using a specific clinical protocol.
- Uterine Artery Doppler: Ultrasound technology to measure the resistance of blood flow to the placenta.
- Maternal Biochemistry: Measuring Placental Growth Factor (PlGF), a protein that directly reflects placental health.
By integrating these three markers, we can predict pre-eclampsia requiring delivery before 34 weeks with approximately 90% sensitivity.
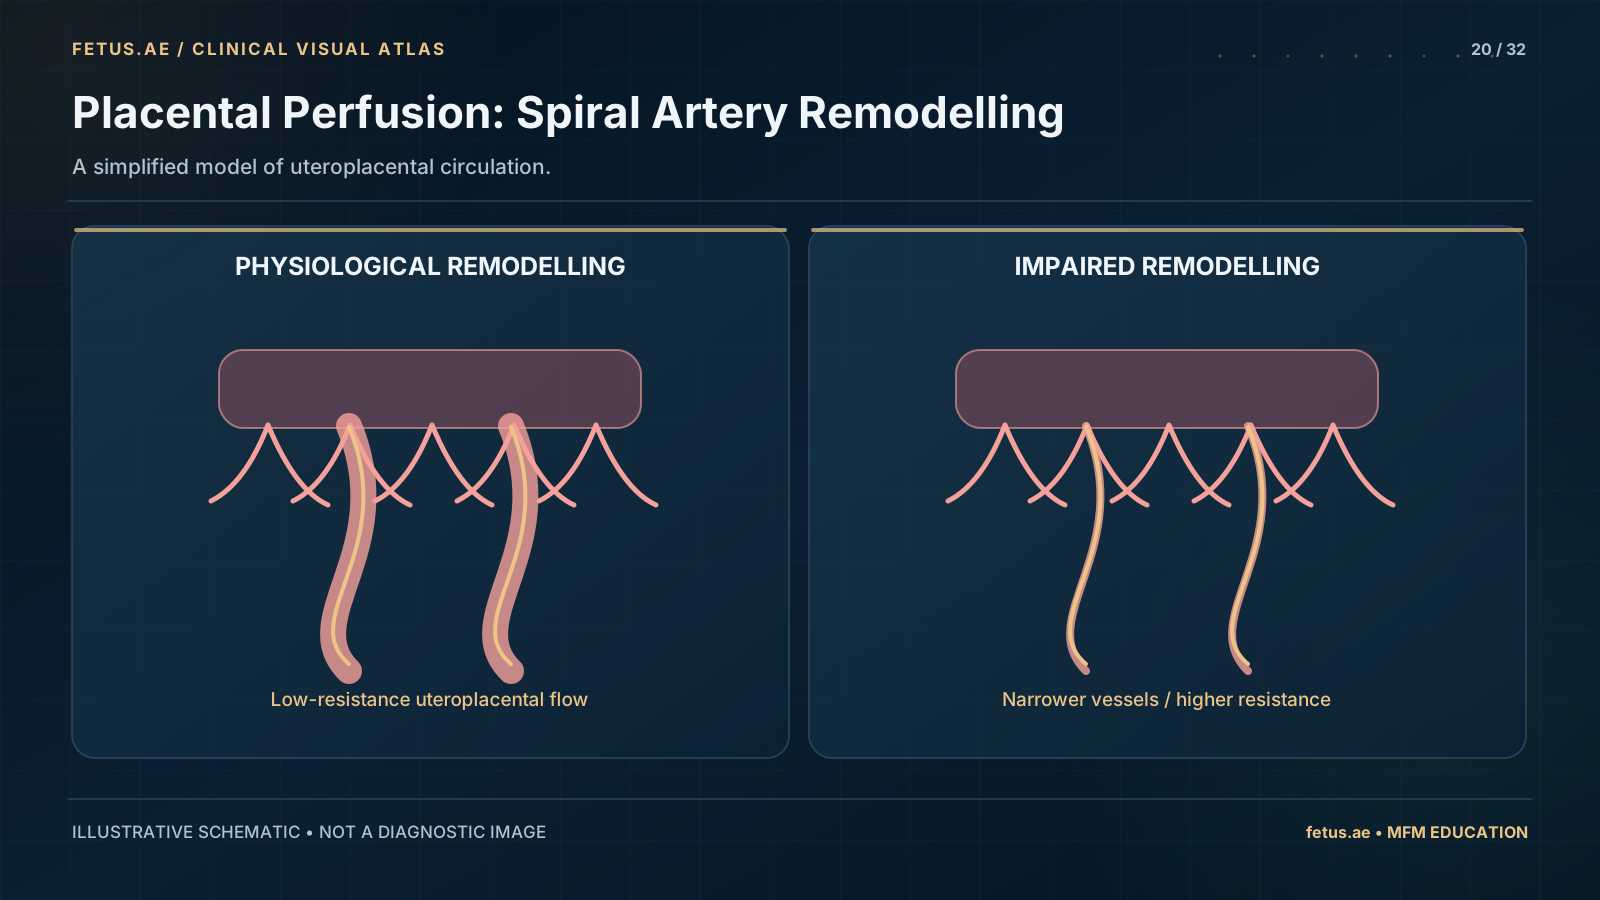 Enlarge schematic
A simplified model of uteroplacental circulation.
Simplified educational schematic; not to scale or for diagnosis.
Universal Screening: Why Every Pregnancy Benefits
Pre-eclampsia risk should be assessed early in pregnancy. Depending on the protocol and resources available, assessment may combine maternal history and characteristics with blood pressure, uterine-artery Doppler, and biochemical markers. Risk is higher with factors such as previous pre-eclampsia, multifetal pregnancy, chronic hypertension, kidney disease, diabetes, or autoimmune disease, but the absence of recognised factors does not eliminate risk. The result informs discussion of prevention and surveillance; it does not diagnose pre-eclampsia.
The Triple Test: MAP, Doppler, and Biochemistry
The screening procedure is seamlessly integrated into your 12-week Nuchal Translucency visit. It is a precise, three-step clinical assessment:
- Precision Biometrics: Your blood pressure is taken twice in each arm by our trained staff using validated equipment. We calculate the Mean Arterial Pressure (MAP), which is a more stable indicator of vascular health than a single reading.
- Advanced Doppler Ultrasound: Our MFM subspecialists use color Doppler to visualize the uterine arteries. We measure the 'Pulsatility Index' (PI) to see how much resistance the blood faces as it tries to enter the placenta. High resistance is a major warning sign.
- Placental Biochemistry: A blood sample is analyzed for PlGF. A healthy, well-embedding placenta produces high levels of PlGF; low levels indicate the placenta is under stress.
A result is considered 'high risk' if the ratio is 1 in 100 or higher. This doesn't mean you have pre-eclampsia; it means you have entered a group that requires active prevention.
 Enlarge schematic
Multiple clinical inputs contribute to an individualized risk estimate.
Simplified educational schematic; not to scale or for diagnosis.
The Window of Opportunity: Aspirin and Prevention
A clinician reviews the overall risk, contraindications and applicable guideline before prescribing aspirin. In ASPRE, 150 mg nightly reduced preterm pre-eclampsia in the selected screen-positive singleton trial population; this is not a universal reduction for all forms of pre-eclampsia. Dose, start and stop dates differ across protocols and should be documented. Aspirin is preventive, not treatment for established disease, and follow-up remains necessary.
Clinical Outcomes: Protecting Mother and Baby
Screening and appropriate prevention can reduce some risks and help plan monitoring. They cannot prevent every case or replace blood pressure checks and symptom assessment. A low-risk screen does not exclude later pre-eclampsia. Discuss when growth or blood-pressure follow-up is due and how to obtain urgent assessment.
Acting Before 16 Weeks: The Critical Deadline
Discuss early risk assessment at booking. The combined first-trimester model has a defined gestational window, but missing it does not make later clinical risk assessment or blood-pressure surveillance useless. Seek urgent assessment for severe headache, visual changes, upper abdominal pain, sudden breathlessness or feeling acutely unwell, including after birth.