Fetal Conditions
Fetal Ventriculomegaly: Measurements, Causes and Care
In brief — the direct answer
Fetal ventriculomegaly means that the atrium of a lateral ventricle, a fluid-filled space in the brain, measures 10 mm or more on ultrasound. It is an imaging finding, not a single disease, and is not automatically hydrocephalus. The outlook depends on the measurement, whether it progresses and whether other findings are present. Isolated mild enlargement often has a favourable outcome after a complete assessment.
What is Fetal Ventriculomegaly: Measurements, Causes and Care?
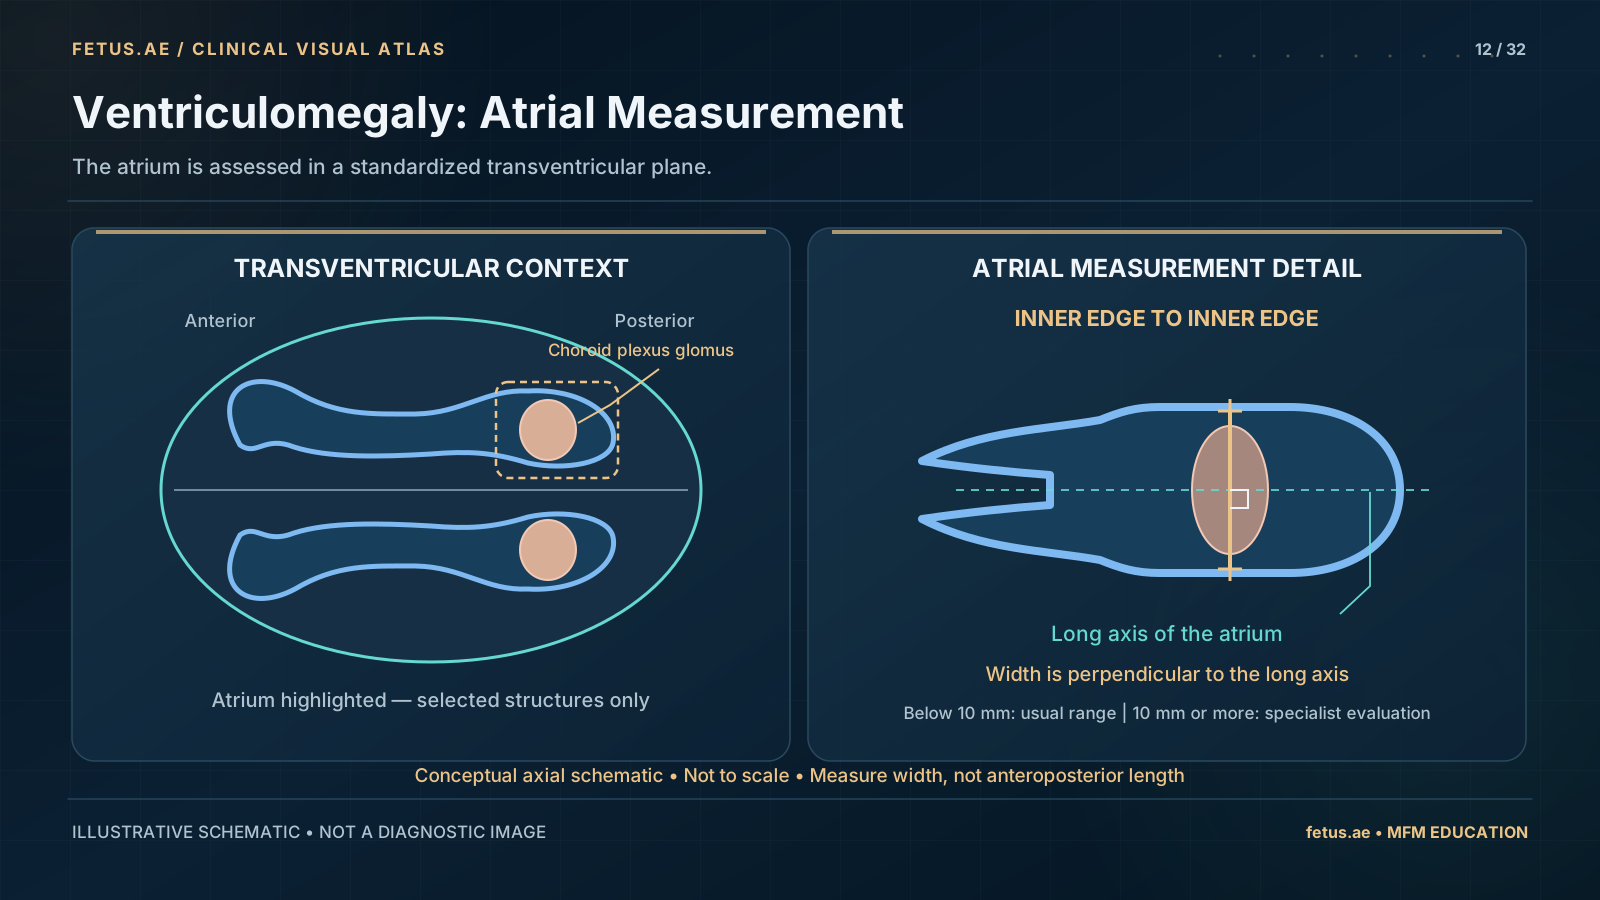
The measured structure is the atrium of the lateral ventricle, not the size of the whole brain. SMFM describes mild enlargement as 10–12 mm, moderate as 13–15 mm and severe as over 15 mm. Measurements near a boundary need expert review of the exact value, technique and local classification; they should not be rounded by parents to decide severity. Ventriculomegaly can have several causes. Hydrocephalus refers to disordered cerebrospinal-fluid circulation and is not interchangeable with every enlarged ventricle.
Who is at risk?
Possible causes include differences in brain development, chromosome or single-gene conditions, CMV or toxoplasmosis infection, and bleeding or altered cerebrospinal-fluid circulation. Some cases remain unexplained after investigation. The findings and family history determine which tests are most useful.
How we diagnose it
Assessment includes a detailed anatomy and specialist brain ultrasound, review of both ventricular measurements and follow-up for progression. Diagnostic testing with chromosomal microarray should be offered, with counselling about what it can and cannot detect. Testing for CMV and toxoplasmosis is recommended even without a known exposure. Fetal MRI may add information in selected cases, depending on prior neurosonography, gestation and expert interpretation. A normal microarray does not exclude all genetic causes.
 Enlarge schematic
The atrium is assessed in a standardized transventricular plane.
Simplified educational schematic; not to scale or for diagnosis.
What does management involve?
There is no single treatment for every enlarged ventricle. Care addresses any identified cause and monitors change over time. Timing and mode of delivery generally follow standard obstetric indications, with additional planning for associated findings or marked head enlargement. Some babies need postnatal imaging, genetics assessment or neurosurgical review. A shunt is considered for selected hydrocephalus cases, not routinely for mild ventriculomegaly.
What are the outcomes?
After a complete evaluation, isolated mild ventriculomegaly has a greater than 90% likelihood of normal neurodevelopment in published counselling guidance. This is a population estimate, not a guarantee for an individual child. Moderate or progressive enlargement and associated structural, infectious or genetic findings change the outlook. Discuss the remaining uncertainty and the postnatal follow-up plan.
When to see a subspecialist
If your doctor has mentioned 'fluid in the brain' or a measurement 'just at the limit' (e.g., 10 or 11 mm), you should be seen by a subspecialist at the MFM Unit.
The expertise required to perform a detailed fetal brain scan is specialized. Our consultants, including Dr. Leanne Bricker, provide the expert neuro-imaging and the evidence-based counseling needed to guide you through the next steps and provide reassurance where it is appropriate.