In brief — the direct answer
Monochorionic diamniotic (MCDA) twins share a placenta but have separate amniotic sacs. Placental vessel connections create risks such as TTTS and TAPS, while growth restriction and other complications also require assessment. Ultrasound surveillance generally starts at 16 weeks and continues at least every two weeks, with additional checks when indicated. Symptoms between visits still need prompt assessment.
What is Twins: MCDA (Monochorionic)?
In MCDA twins, 'monochorionic' means one chorion (placenta). On ultrasound before 14 weeks, we identify this by the 'T sign'—a very thin membrane that meets the placenta at a 90-degree angle, without the thick wedge seen in DCDA twins. Because the babies share a single blood pool, their destinies are linked; what happens to one can affect the blood pressure and oxygen levels of the other.
VISUAL EXPLORER
Understanding a twin pregnancy
Choose a topic to compare selected placental patterns and shared-placenta complications.
Ultrasound assessment establishes how many placentas and amniotic sacs are present. This helps plan surveillance. Two placentas can appear fused; the illustration cannot classify an individual pregnancy.
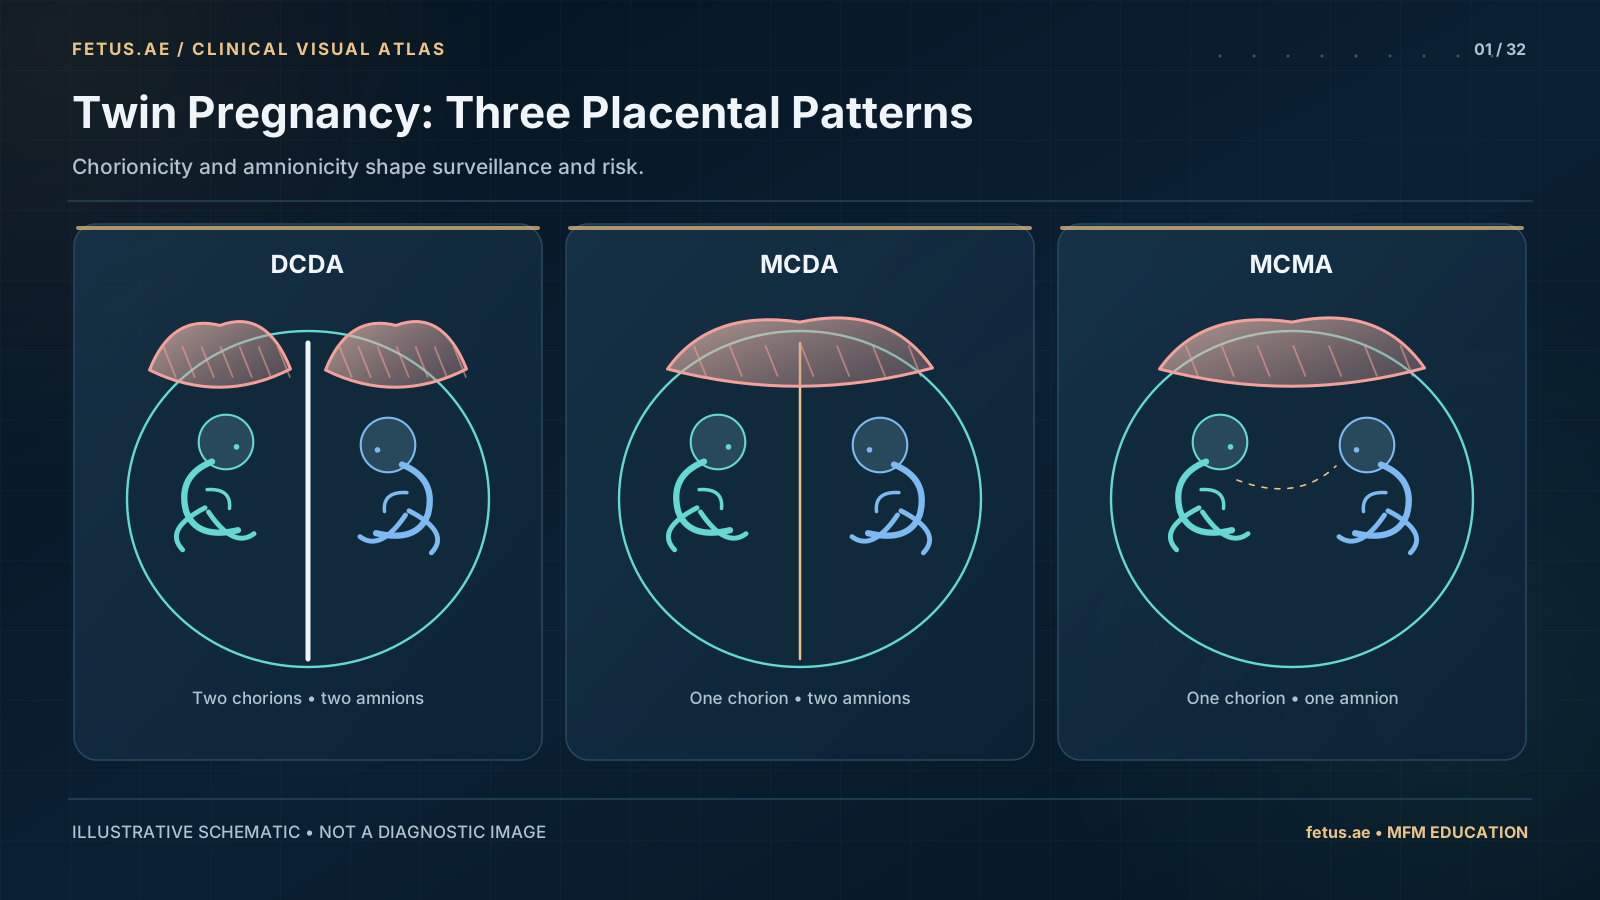 Enlarge schematic
Chorionicity and amnionicity shape surveillance and risk.
Simplified educational schematic; not to scale or for diagnosis.
Educational selector. Individual ultrasound findings and specialist review determine the care plan.
Who is at risk?
MCDA twins are at risk for specific 'shared-placenta' complications:
- TTTS (Twin-to-Twin Transfusion Syndrome): When one baby sends too much blood to the other.
- sFGR (Selective Fetal Growth Restriction): When the placenta is shared unequally, and one twin becomes much smaller.
- TAPS (Twin Anemia Polycythemia Sequence): A slow, chronic blood transfusion between the babies.
- Sudden Events: Because of the connected vessels, if one baby experiences a sudden event, the other is at immediate risk.
How we diagnose it
The management of MCDA twins relies on frequent, high-resolution ultrasound:
- Bi-weekly Scans: Starting at 16 weeks, we scan every 14 days without exception.
- Amniotic Fluid Check: Measuring the 'Deepest Vertical Pocket' (DVP) in each sac to check for TTTS.
- Bladder Assessment: Confirming both babies have visible bladders.
- Doppler Studies: Checking the blood flow in the brains and umbilical cords of both babies.
What does management involve?
Our care follows the highest international standards:
- Standardized Reporting: Every scan tracks the difference in weight and fluid between the twins.
- Fetal Surgery Readiness: If TTTS or TAPS is detected, we are one of the few centers in the region capable of performing Fetoscopic Laser Ablation to separate the shared blood vessels.
- Cervical Surveillance: Monitoring the mother for signs of early labor, which is more common in twin pregnancies.
What are the outcomes?
With early detection, most shared-placenta twins have a safe arrival:
- Timing: We typically recommend delivery at 36 weeks. Waiting longer increases the risk of placental insufficiency in these shared gestations.
- Mode of Delivery: If both babies are growing well and the first twin is head-down, a vaginal birth is possible. However, the threshold for a C-section is lower than in singleton pregnancies to ensure the safest exit for both twins.
When to see a subspecialist
If your early scan shows 'identical' twins or 'single placenta,' you should be referred to a fetal medicine specialist immediately.
Dr. Werner Diehl and Dr. Ali Al-Ibrahim specialize in monochorionic twin pathology. We provide the bi-weekly, high-precision scans necessary to identify complications early and the surgical expertise to treat them if they occur.