In brief — the direct answer
Fetoscopic laser surgery closes connecting vessels on a shared placenta to treat selected twin-to-twin transfusion syndrome (TTTS) cases. Stage, gestation, symptoms and findings in both twins guide the decision. Laser addresses the placental connections but does not guarantee survival or remove the need for surveillance of recurrence, TAPS, growth and preterm birth.
Placental Plumbing: What is Fetoscopic Laser Ablation?
In pregnancies where identical twins share a single placenta, they also share 'plumbing.' Naturally occurring connections between their blood vessels (anastomoses) are usually balanced. However, in TTTS, these connections become one-way. This creates a 'donor' twin who gives away too much blood and a 'recipient' twin who receives too much.
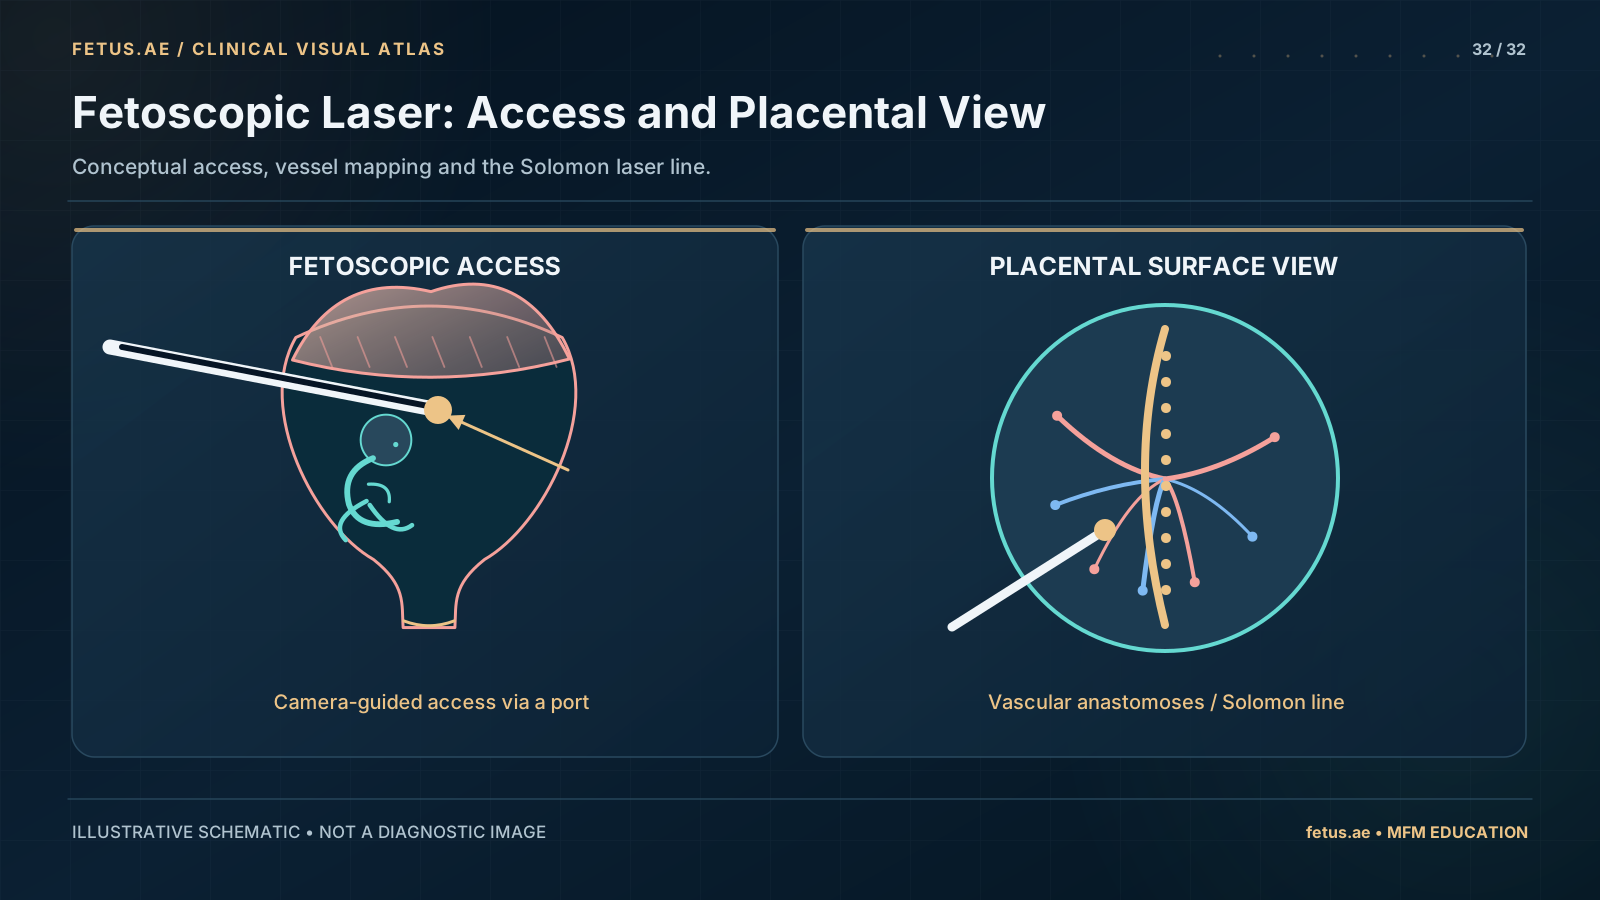
Fetoscopic laser ablation is the only way to fix this mechanical plumbing error. Using a thin telescope (fetoscope), we enter the amniotic sac and visualize the surface of the shared placenta. We then identify every single connecting vessel and use laser energy to seal them. This effectively 'divides' the shared placenta into two separate, independent territories. In our Unit, we utilize the Solomon Technique, which involves drawing a laser line across the entire placental equator to ensure no hidden connections are missed, significantly improving long-term outcomes and preventing recurrence.
 Enlarge schematic
Conceptual access, vessel mapping and the Solomon laser line.
Simplified educational schematic; not to scale or for diagnosis.
Critical Indicators: When is Laser Surgery Required?
This procedure is not a 'choice' but a medical necessity for pregnancies where the biological balance of twin development has failed. It is primarily indicated for:
- TTTS (Stage II, III, or IV): When there is a visible fluid imbalance (too much in one, too little in the other) or abnormal blood flow detected via Doppler.
- TAPS (Twin Anemia Polycythemia Sequence): A slower, more subtle transfusion where one twin becomes severely anemic while the other becomes 'thick-blooded' (polycythemic).
- Twin Reversed Arterial Perfusion (TRAP): Where an acardiac twin's blood supply is provided by a pumping twin.
The procedure is most successful when performed between 16 and 26 weeks of pregnancy, before the physiological stress on the babies' hearts becomes irreversible.
Mapping the Equator: The Precision of Pre-Surgical Planning
The path to laser surgery requires extreme diagnostic precision. Before we even enter the operating room, our subspecialists perform a comprehensive 'placental mapping' session:
- Staging Review: We use Quintero Staging to determine the severity. This involves measuring the 'Deepest Vertical Pocket' (DVP) of fluid and verifying the visibility of the donor twin's bladder.
- Hemodynamic Doppler Survey: We measure blood flow in the umbilical arteries, the ductus venosus, and the middle cerebral arteries of both babies to assess cardiac stress.
- Cervical Integrity: We measure the mother's cervix to assess the risk of premature labor and to plan the surgical entry point.
This data allows us to transition from 'suspected TTTS' to a definitive surgical plan in a matter of hours.
The Solomon Technique: A Masterclass in Fetal Surgery
At the MFM Unit, laser ablation is performed in a specialist fetal therapy setting. The process is designed for safety and minimal disruption:
- Precision Entry: The mother is typically given local anesthesia with light sedation. A 3mm fetoscope is inserted through the abdomen into the amniotic sac of the recipient twin.
- Direct Visualization: We view the placenta 'live' on a high-definition monitor, identifying the distinct vascular network of each twin.
- The Laser Barrier: Using the Solomon method, we do not just 'spot weld' individual vessels; we create a continuous laser line (a new equator) across the entire placenta.
- Fluid Volume Restoration: We finish by performing an 'amnioreduction,' removing the excess fluid from the recipient twin to reduce pressure on the uterus and the risk of early water breaking.
Post-surgical care is just as critical; mothers remain for 24-hour observation with continuous monitoring of the fetal heartbeats to ensure a smooth transition to the 'new' placental environment.
 Enlarge schematic
A schematic overview of placental vessel interruption.
Simplified educational schematic; not to scale or for diagnosis.
The Gift of Independence: Survival and Long-Term Success
Outcome varies with stage, gestation, associated findings and response to treatment. Fetoscopic laser is established treatment for stage II–IV TTTS presenting at 16–26 weeks; stage I and presentations outside that window need individual assessment. Published survival estimates must not be represented as this unit’s audited results. Risks include membrane rupture, preterm birth, loss of one or both twins, recurrent TTTS, TAPS and neurological injury. Continued follow-up is essential even after technically successful surgery.
The Rapid Response: Timing in Monochorionic Twin Care
Suspected TTTS requires prompt assessment by a fetal-therapy centre. Bring the chorionicity report, fluid measurements, bladder findings and Doppler results if available. Referral should not wait for a later stage. Sudden abdominal enlargement, breathlessness, pain, contractions or reduced movements needs urgent maternity assessment.