In brief — the direct answer
Intrauterine transfusion treats selected severe fetal anaemia by giving appropriately prepared donor red cells under ultrasound guidance. It may improve anaemia and hydrops and allow pregnancy to continue, but repeat procedures may be needed and procedural risks remain. The cause, gestation and fetal condition guide treatment and birth planning.
What is Intrauterine Transfusion (IUT)?
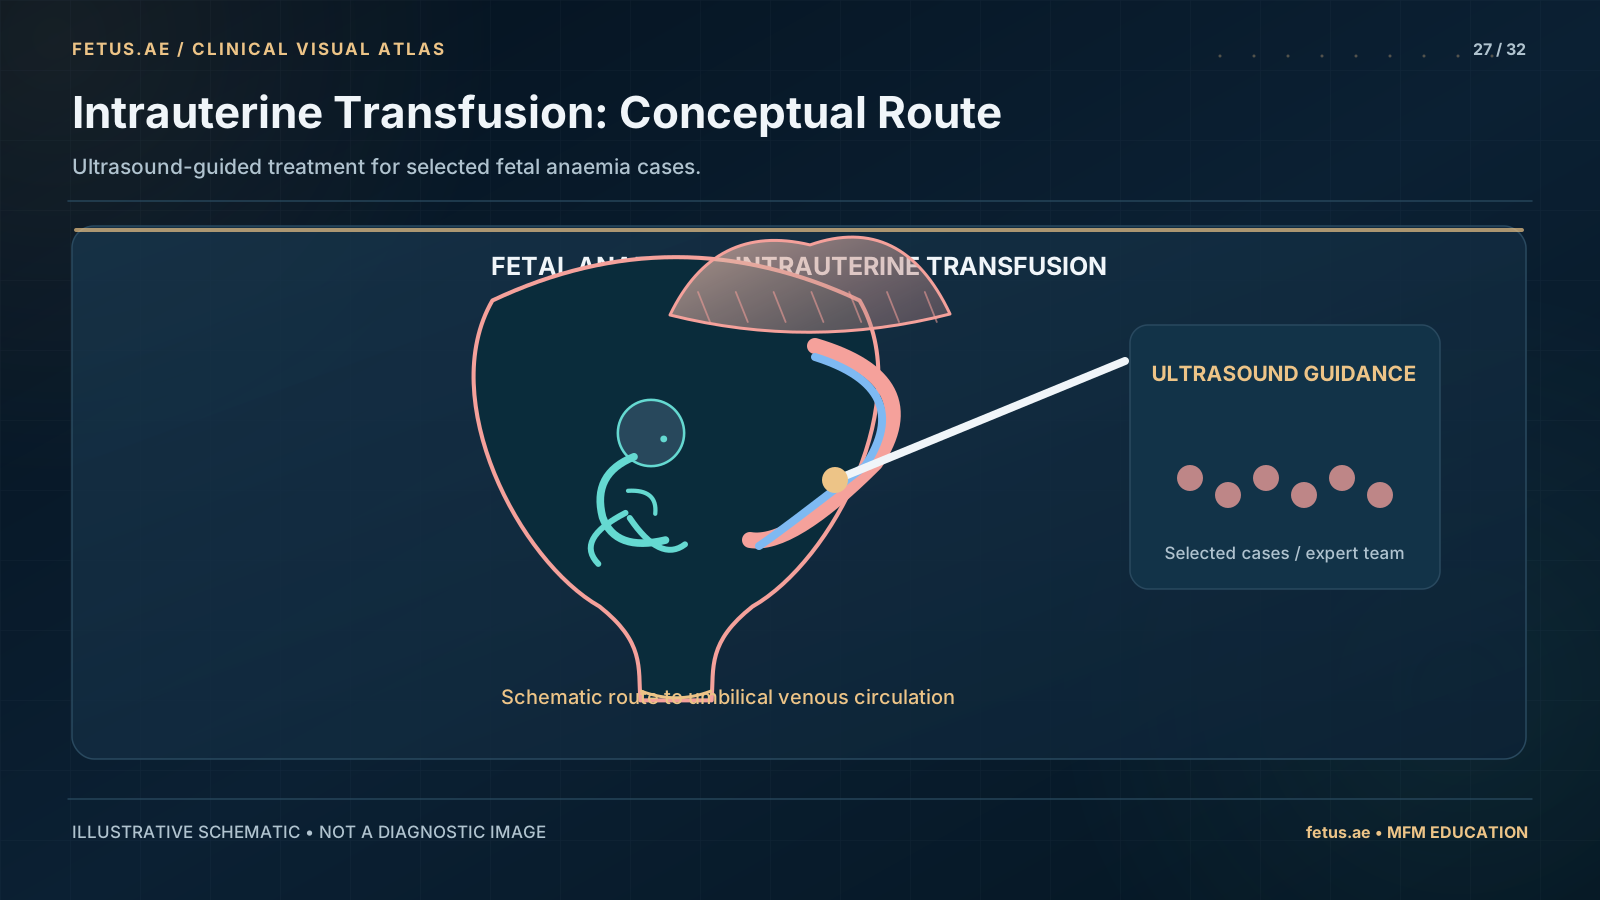
The procedure involves passing a fine needle through the mother's abdomen and into the baby's umbilical cord, specifically the umbilical vein.
Before the procedure, our laboratory prepares a unit of 'O-negative' blood that has been cross-matched with the mother's blood, irradiated (to prevent immune reactions), and 'packed' so that a small volume provides a high concentration of red blood cells. This ensures we don't 'overload' the baby's heart while still giving them enough blood to thrive.
Who is at risk?
IUT is indicated when non-invasive monitoring (MCA Doppler) shows that the baby is significantly anaemic. Without this procedure, severely anaemic babies can develop Hydrops Fetalis (fluid buildup) and may not survive. The procedure can be performed as early as 16-18 weeks of pregnancy and as late as 35 weeks.
How we diagnose it
Before the needle is inserted, we perform a 'Final Check':
- Doppler Mapping: Locating the best entry point into the umbilical cord (usually where it attaches to the placenta).
- Hemoglobin Calculation: Based on the baby's gestation and the current MCA Doppler speed, we calculate the exact volume of blood the baby needs (usually between 30ml and 100ml).
- Fetal Positioning: Ensuring the baby is in a stable position, sometimes using a temporary muscle relaxant for the baby so they don't move during the needle placement.
What does management involve?
The procedure follows a precise sequence:
- Access: Under local anesthesia for the mother, the needle is guided into the umbilical vein.
- Blood Sampling: First, a small sample of the baby's blood is taken to confirm the exact hemoglobin level (Cordocentesis).
- The Transfusion: The prepared blood is slowly pushed through the needle manually by the surgeon. We watch the baby's heart rate continuously on the monitor.
- Post-Care: We take a final sample to confirm the new, healthy blood level. The needle is then removed, and the mother is monitored for 4-6 hours in our recovery suite.
 Enlarge schematic
Ultrasound-guided treatment for selected fetal anaemia cases.
Simplified educational schematic; not to scale or for diagnosis.
What are the outcomes?
The medical success of IUT is outstanding.
- Recovery: Within 24-48 hours, the baby's heart function often improves, and their movement increases.
- Resolution of Hydrops: If the baby had fluid buildup, it usually begins to disappear within a week of the first transfusion.
- Birth: Most babies who receive IUTs are born healthy at 34-36 weeks. They may have jaundice (yellow skin) after birth, but this is easily treated with blue-light therapy (phototherapy) in the NICU.
When to see a subspecialist
Arrange prompt fetal-medicine review for a concerning red-cell antibody result, suspected fetal anaemia or an abnormal MCA peak systolic velocity. Fetal blood sampling and transfusion require an experienced team, suitable blood-bank support and an individual consent discussion. Published procedural success and safety estimates should be distinguished from a centre’s own audited results. Reduced movements or maternal deterioration needs urgent maternity assessment.