In brief — the direct answer
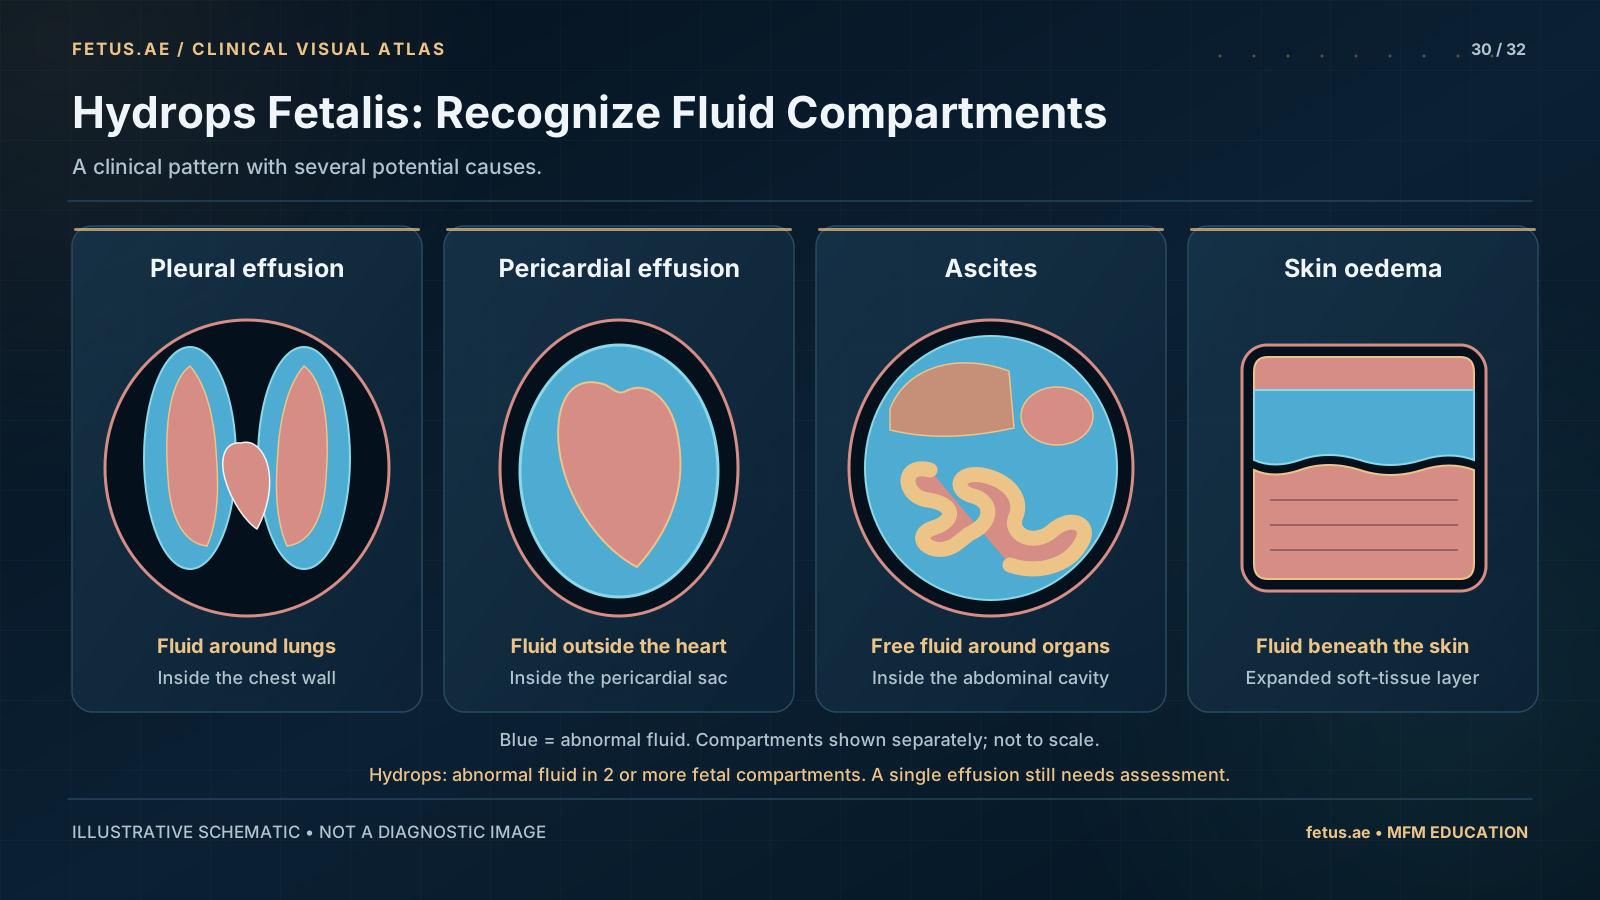
Hydrops fetalis is abnormal fluid in at least two fetal compartments, such as under the skin, in the abdomen or around the lungs or heart. It is a serious finding with many possible causes, not a single diagnosis. Prompt fetal-medicine assessment should investigate treatable causes and check maternal wellbeing. Even one unexplained fetal fluid collection can warrant detailed investigation; do not wait for a second to appear.
What is Hydrops Fetalis?
An immune cause results from maternal antibodies affecting fetal red cells. Non-immune causes include genetic conditions, structural heart disease, arrhythmias, anaemia, infection, lymphatic disorders and complications of a shared placenta. More than one mechanism can be involved. The finding alone does not determine whether treatment is possible or predict the individual outcome.
 Enlarge schematic
A clinical pattern with several potential causes.
Simplified educational schematic; not to scale or for diagnosis.
Who is at risk?
Hydrops may occur with or without a previous risk factor. Review maternal red-cell antibodies, relevant infections, fetal anatomy and rhythm, family history and placental findings. RhD-negative blood type alone does not mean immune hydrops; the antibody assessment matters. Anti-D prevents sensitisation in eligible patients but does not treat established fetal anaemia.
How we diagnose it
The workup combines detailed ultrasound, fetal cardiac and rhythm assessment, Doppler for anaemia and targeted maternal tests. SMFM’s 2026 guidance recommends offering diagnostic testing including chromosomal microarray when one or more fetal effusions are detected. Infection PCR is considered when relevant. When chromosome testing is non-diagnostic, exome or genome sequencing should be discussed in the appropriate setting, with counselling about uncertain results and residual diagnostic limitations.
What does management involve?
Treat a specific cause when evidence and eligibility support it: fetal transfusion for selected anaemia, medication for some arrhythmias or drainage/shunting for selected chest effusions. Not every case is treatable in the womb. Maternal assessment is essential because mirror syndrome can cause dangerous swelling, hypertension and organ dysfunction. Delivery timing, neonatal treatment and all available pregnancy-care options require individual multidisciplinary counselling and attention to maternal risk, family preferences and local requirements.
What are the outcomes?
The outlook varies widely with the cause, gestation, associated findings, response to treatment and severity. A single survival percentage is misleading. Discuss the likely benefit and risks of any intervention, the chance that the cause remains uncertain, neonatal intensive-care needs and appropriate follow-up. Improvement in fluid does not by itself exclude an underlying condition.
When to see a subspecialist
Arrange urgent fetal-medicine assessment for hydrops or an unexplained fetal fluid collection. If the mother develops sudden swelling, breathlessness, severe headache, visual symptoms or feels acutely unwell, seek urgent maternity/emergency assessment. Bring ultrasound, antibody, infection and genetic reports; investigations can proceed in parallel rather than waiting for one result before considering the next.