In brief — the direct answer
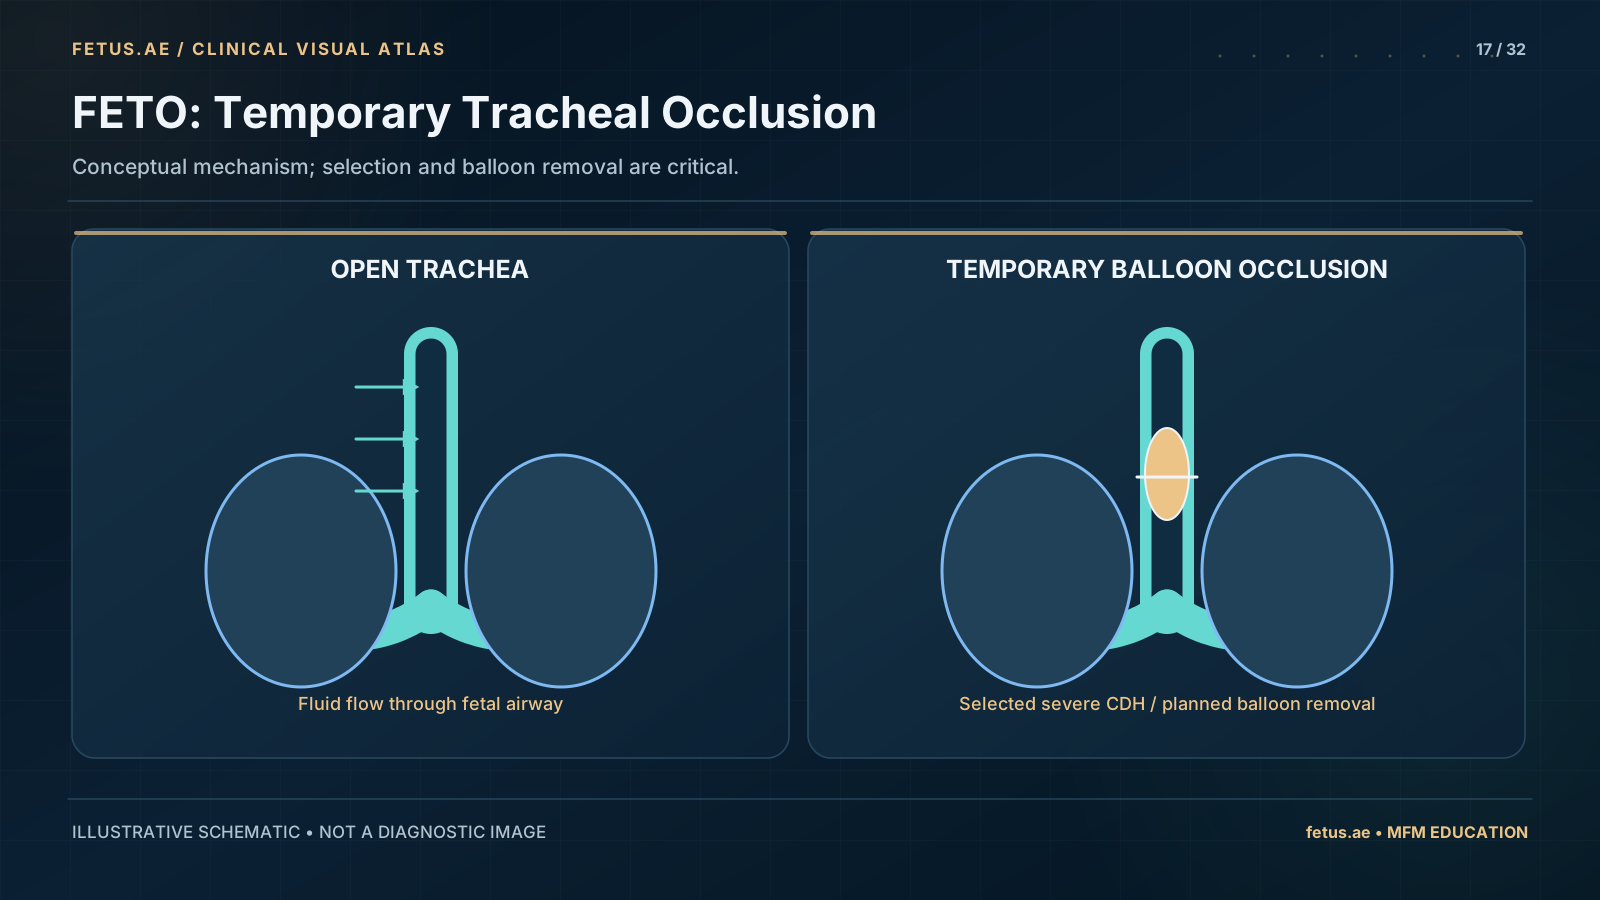
Fetoscopic endoluminal tracheal occlusion (FETO) temporarily blocks the fetal windpipe with a balloon to stimulate lung growth in selected congenital diaphragmatic hernia cases. It does not close the diaphragm defect. Eligibility depends on the side and severity of CDH, associated findings, maternal factors and the treating centre’s protocol. The balloon must be removed before birth, with an emergency retrieval plan in place.
What is The FETO Procedure?
The procedure is divided into two phases:
- Balloon Insertion (Occlusion): Performed between 27 and 29 weeks of pregnancy. A tiny balloon is placed in the windpipe to start the growth phase.
- Balloon Removal (Reversal): Performed around 34 weeks. The balloon is removed to allow the lungs to 'deflate' slightly and prepare for the baby's first breath at birth.
The goal is not to fix the hole in the diaphragm (which is done after birth), but to ensure the baby has enough lung volume to breathe while the surgeons work.
Who is at risk?
Assessment includes expert observed-to-expected lung-to-head ratio measurement, liver position, detailed anatomy, genetic evaluation and, when helpful, MRI. Evidence from severe isolated left-sided CDH cannot automatically be applied to moderate or right-sided disease. Discuss candidacy, procedural timing and the ability to stay close to a centre capable of urgent balloon removal.
How we diagnose it
Before the procedure, several checks are essential:
- Fetoscopic Planning: Mapping the location of the baby's face and the safest entry point into the amniotic sac.
- Balloon Selection: We use a 'Goldbal'—a microscopic latex balloon that is filled with saline.
- Maternal Preparation: The mother is given a course of steroids to help mature the baby's lungs and reduce the risk of premature delivery.
What does management involve?
The insertion procedure is performed under local anesthesia and sedation:
- Entry: A thin tube (trocar) is passed through the mother's abdomen into the amniotic fluid.
- Navigating the Airway: Using a 1.2mm fetoscope (like a tiny camera), the surgeon navigates through the baby's mouth and vocal cords into the trachea.
- Inflation: The balloon is inflated inside the trachea and detached. The entire process is visible on a high-definition screen.
- Balloon Removal: This is equally important and can be done fetoscopically, via a small needle puncture (ultrasound-guided), or in an emergency at birth (EXIT procedure).
 Enlarge schematic
Conceptual mechanism; selection and balloon removal are critical.
Simplified educational schematic; not to scale or for diagnosis.
What are the outcomes?
The TOTAL randomised trials found a survival benefit in the selected severe left-sided group, while the moderate-disease trial did not demonstrate a statistically significant benefit in its primary outcomes. FETO increases the risk of membrane rupture and preterm birth. It does not eliminate pulmonary hypertension, the need for neonatal intensive care or postnatal diaphragm repair. Published trial results are not local audited outcomes.
When to see a subspecialist
Referral for FETO must be timely. The ideal window for assessment is between 24 and 26 weeks, as the surgery must be performed by 29 weeks to be most effective.
Our Unit provides a rapid-response triage for CDH diagnosis. Families meet with our fetal surgeons and pediatric surgical partners to discuss the technical aspects and the postnatal roadmap. Dr. Werner Diehl's fellowship training at leading European centers ensures that our techniques match the highest global benchmarks.
Questions to ask your doctor
References & Clinical Guidelines
- Randomized Trial of Fetal Surgery for Severe Left Diaphragmatic Hernia
- Randomized Trial of Fetal Surgery for Moderate Left Diaphragmatic Hernia
- TOTAL trials: randomised evidence for FETO in severe and moderate left-sided congenital diaphragmatic hernia
- Updated Practice Guidelines: performance of the routine mid-trimester fetal ultrasound scan